
Facing cataract surgery, most patients find themselves stuck on the same question: with so many intraocular lens options on the market, how do they actually differ? Does paying more always mean seeing better? And what happens if you pick the wrong one?
The honest answer is that lens choice is not a simple multiple-choice question. It is a personalized medical decision that has to take several factors into account at once. Working through the logic clearly is the only way to land on the lens that genuinely fits your life.
Choosing an intraocular lens is a lot like choosing eyeglasses. If the prescription is wrong, even the most expensive lens will give you a headache. The point of replacing your cloudy lens is to help you see clearly, comfortably, and durably in daily life — not to buy the most expensive technology available.
Three Questions to Ask Yourself First
Before you look at any brand or price tag, answer three questions honestly. They will set the boundaries of what is actually suitable for you.
Do I spend more of my day looking at the distance (driving, watching television) or at near (reading, phone, paperwork)?
Am I comfortable wearing reading glasses or a mild prescription correction after surgery if it means the result is more reliable?
Do I have any significant retinal disease — macular degeneration, advanced glaucoma, or diabetic retinopathy?
Your answers will directly narrow the set of lens options you can realistically consider.
The Three Functional Families of IOLs
Even though dozens of products exist, they group into three families by how they handle light.
1. Monofocal IOLs — "The Practical Default"
Monofocal lenses focus light at a single distance (usually far). They are the most affordable and the most predictable. They suit patients with limited budget, or those whose visual needs are modest — for example, patients who are comfortable wearing near-vision glasses for reading and phone use after surgery. The trade-off is exactly that: clear distance vision, with reading glasses needed for close work.
2. Bifocal IOLs — "The Balanced Mid-Tier"
Bifocal lenses split incoming light into two focal points — distance and near. They are well suited to retired patients whose days are mostly made up of either looking far away or reading up close. The trade-off is the intermediate zone: a computer screen, a car dashboard, or a price tag at arm's length may still feel less crisp than the two ends of the range.
3. Trifocal and Extended-Depth-of-Focus IOLs — "The Premium Choice"
Trifocal and extended-depth-of-focus (EDOF) lenses stretch usable focus across the full range — far, intermediate, and near — so most patients can do daily life without reaching for glasses at all. They suit younger patients, those with high quality-of-life expectations, and people who really do not want to depend on spectacles. The trade-offs are price, plus stricter ocular requirements: corneal astigmatism must be small and the retina must be healthy for the optical design to deliver its full benefit.
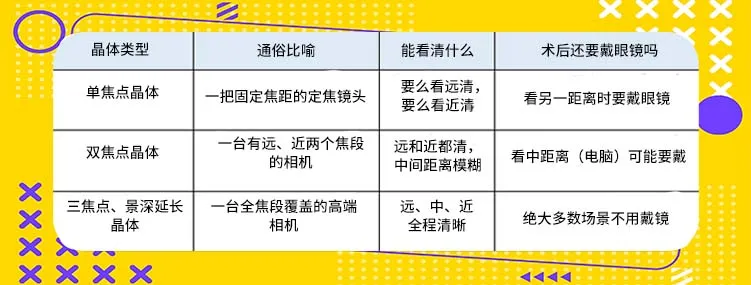
Comparison of monofocal, bifocal, and trifocal / extended-depth-of-focus IOLs by everyday use case and post-surgery spectacle need.
If You Have Astigmatism, the Equation Changes
If your pre-operative examination reveals 1.0 diopter or more of regular corneal astigmatism, every lens family above needs to be considered in its "toric" version — designed to correct astigmatism at the same time as replacing the cloudy lens. Without that correction, post-operative vision can carry ghosting or doubling, and even the most expensive multifocal lens will not perform as designed.
Confirming your astigmatism status during the pre-operative work-up is therefore a key decision point — not a footnote.
When Multifocal IOLs Are Not Appropriate
Multifocal IOLs are designed for patients with healthy eyes. They are not for everyone. In the following situations, surgeons usually recommend a monofocal lens instead.
Advanced glaucoma with visual field loss. Multifocal designs split incoming light into several foci, which reduces contrast. For a patient whose contrast is already compromised, that can make vision feel more tiring rather than better.
Significant macular disease or diabetic retinopathy. If the retina itself cannot produce a sharp image, no lens upgrade will recover that loss.
Irregular corneal astigmatism or severe dry eye. If light is already distorted on its way into the eye, even the most sophisticated lens cannot correct what comes next.
The principle is simple: multifocal lenses are "icing on the cake," not "firewood in winter." Underlying ocular health is the hard constraint on lens choice.
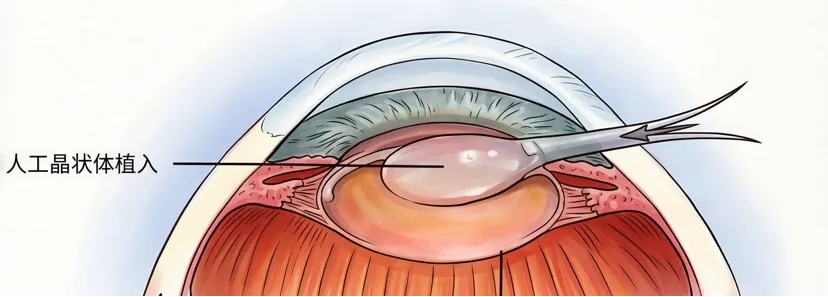
During cataract surgery, the cloudy lens is removed and a chosen intraocular lens is implanted in its place.
Three Rules for a Sound Decision
1. The Pre-Operative Examination Is the Foundation
Your surgeon will measure corneal astigmatism, pupil size, kappa angle, and other objective parameters to define the safe range of lens options for you. Lifestyle and budget choices are then made within that medically defined range — not the other way around.
2. The Two Eyes Can Be Designed Differently
If the two eyes have different baseline conditions, it is perfectly reasonable to implant a multifocal lens in the dominant eye and a monofocal lens in the non-dominant one. The brain integrates the two inputs smoothly, and binocular cooperation can deliver very good distance-to-near vision with fewer compromises than a uniform upgrade.
3. Be Rational About Country of Origin and Price
There is no need to chase "imported" or "expensive" on faith. The technical gap between leading domestic and imported IOLs has narrowed significantly, and every approved product on the market has cleared the same regulatory bar. What matters is whether the optical design fits your visual habits — not the label on the box.
The Decision Framework in One Line
A sound IOL choice follows a simple sequence: first the ocular baseline (retina, optic nerve, cornea), then the lifestyle (driving, screens, reading), and only then the budget. The decision sits where all three intersect.
At Shanghai HePing Eye Hospital, our cataract team provides a structured pre-operative work-up, walks international patients through the realistic trade-offs of each lens family, and supports both monofocal and premium IOL options including multifocal and toric designs. Contact us to plan a cataract consultation that fits your eyes and your daily life.